
Table of Contents
- Understanding Testosterone Therapy and Cardiovascular Risk
- What Recent Clinical Trials Reveal About TRT Safety
- Cardiovascular Safety of Testosterone Replacement Therapy: Key Findings
- Heart Attack, Stroke, and Other Cardiovascular Risks
- Testosterone Therapy Monitoring Protocols: Protecting Your Heart
- Benefits of Medically Supervised TRT and Risk Mitigation
- Making an Informed Decision About Testosterone Therapy
- Frequently Asked Questions
Last Updated: September 28, 2026
Understanding Testosterone Therapy and Cardiovascular Risk
Testosterone therapy heart health risks are heavily debated. The real question is whether the risks of testosterone replacement therapy outweigh the benefits for men with low testosterone, and what monitoring protocols can mitigate those risks. (Source: landmark TTrials study)
Over the past decade, early concerns about testosterone therapy have been challenged by newer clinical trials, yet legitimate cardiovascular risks remain. Understanding what the research actually shows is essential for men considering treatment.
Cardiovascular safety depends on baseline health, dosage, monitoring frequency, and individual risk factors. Men with existing heart disease, hypertension, or metabolic syndrome face different risk profiles than those with normal baseline screening results.
What Recent Clinical Trials Reveal About TRT Safety
The landmark TTrials study found that testosterone therapy did not increase major cardiovascular events in men with baseline screening showing no significant coronary artery disease, contradicting earlier observational studies that had raised alarms about myocardial infarction risk.
However, the TTrials study excluded men with a history of heart disease, stroke, or significant coronary artery disease. For men with pre-existing cardiovascular disease, studies show mixed results, with some suggesting increased risk of acute cardiovascular events during the first months of therapy.
Baseline cardiovascular assessment matters more than testosterone therapy heart health considerations themselves. Men who undergo proper screening before starting treatment, including EKG, lipid panels, and coronary artery disease risk assessment, show better safety outcomes. This is why a lab-first approach to testosterone therapy monitoring protocols is critical before initiating treatment.
Cardiovascular Safety of Testosterone Replacement Therapy: Key Findings
Testosterone affects the cardiovascular system through multiple pathways: vascular function, inflammation, lipid metabolism, and cardiac electrolyte balance. Understanding these mechanisms explains why some men tolerate therapy well while others face complications.
Some studies suggest testosterone therapy may increase arrhythmia risk, particularly in older men or those with underlying cardiac vulnerability. However, the absolute incidence remains low in properly screened populations. Men with normal baseline cardiac function and no arrhythmia history rarely develop atrial fibrillation during testosterone therapy with appropriate dosing and monitoring.
Short-Term vs. Long-Term Risk Profiles
The first 3-6 months of testosterone therapy carry the highest cardiovascular risk, when rapid hormonal shifts, hematocrit elevation, and vascular remodeling occur simultaneously. After this acute phase, the risk profile stabilizes considerably in men on stable, monitored doses. Long-term therapy in properly screened men shows cardiovascular event rates comparable to untreated hypogonadal men in some studies.
Men considering short-term therapy (12-24 months) face different risk calculus than those committing to indefinite replacement. Short-term therapy allows conservative dosing and intensive monitoring during the highest-risk window, with the option to discontinue if side effects emerge.
Left Ventricular Hypertrophy and Cardiac Remodeling
Left ventricular hypertrophy (thickening of the heart’s main pumping chamber) can result from testosterone therapy. Regular monitoring through EKG and echocardiography in men on long-term therapy helps detect this early, allowing dose adjustments before it becomes clinically significant.
Physiologic left ventricular hypertrophy differs from pathologic hypertrophy driven by hypertension or excessive hormone exposure. Men receiving physiologic replacement doses (typically 100-200 mg weekly) rarely develop significant left ventricular thickening. This underscores why dose selection and blood pressure control directly influence cardiac safety.
Lipid Changes and Metabolic Mitigation
High-density lipoprotein cholesterol typically decreases during testosterone therapy by 10-15%, while triglycerides may increase modestly. Regular lipid panel monitoring allows providers to adjust therapy or recommend lifestyle interventions before lipid changes become problematic.
Men experiencing unfavorable lipid shifts have concrete options. Increased aerobic exercise (150 minutes weekly) improves HDL and reduces triglycerides. Dietary modifications, reducing refined carbohydrates, increasing soluble fiber, limiting saturated fat, produce measurable improvements. Fish oil supplementation (2-3 grams daily of EPA/DHA) addresses triglyceride elevation. Statin therapy can be added if lifestyle measures prove insufficient.
Heart Attack, Stroke, and Other Cardiovascular Risks
The risk of myocardial infarction and stroke depends primarily on baseline cardiovascular health and underlying risk factors. Men with hypertension, diabetes, smoking history, or family history of early cardiac events face higher absolute risk. Testosterone therapy modulates existing risk based on individual physiology.
Acute cardiovascular events cluster in the first three to six months of treatment, suggesting rapid hormonal changes pose the greatest risk. This supports conservative dosing and frequent monitoring during early treatment. Men with multiple risk factors benefit from stress testing before starting therapy.
Peripheral artery disease risk appears modestly elevated in some testosterone users, though absolute incidence remains low. Men with leg pain with exertion, claudication, or other vascular symptoms warrant vascular assessment before starting therapy.
Higher testosterone doses carry greater cardiovascular risk than physiologic replacement doses. Men receiving 200mg weekly face different risk profiles than those receiving 100mg weekly. Medically supervised TRT uses doses designed to restore testosterone to normal physiologic ranges rather than supraphysiologic levels.
Testosterone Therapy Monitoring Protocols: Protecting Your Heart
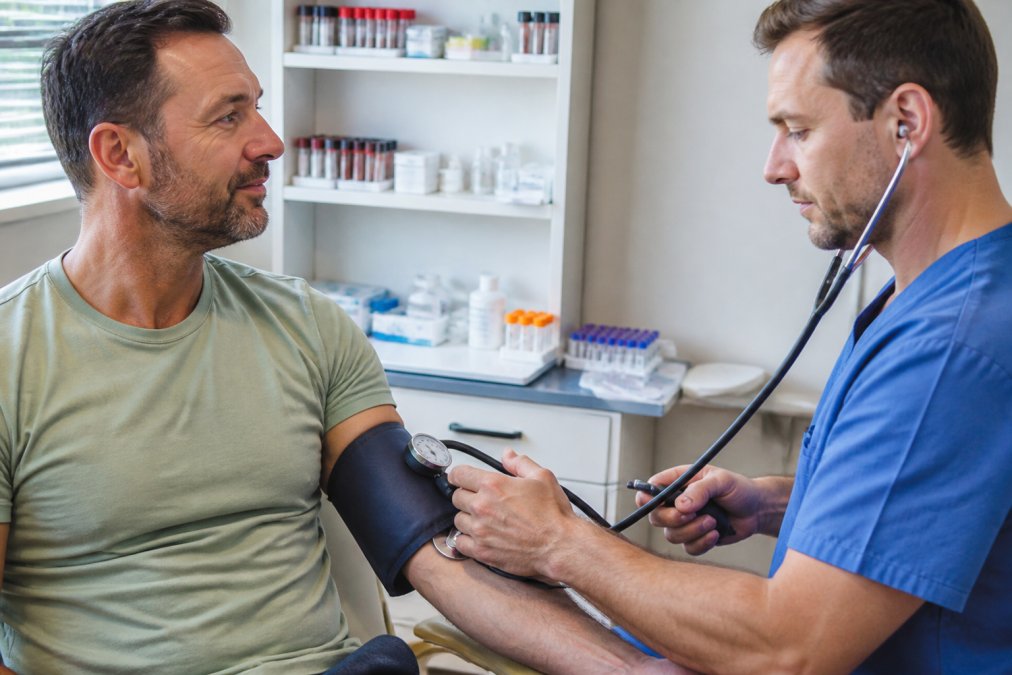
Monitoring protocols begin before treatment starts. Baseline screening should include comprehensive metabolic panel, lipid panel, EKG, and cardiovascular risk assessment. Men with significant risk factors may benefit from stress testing or imaging to establish baseline coronary status.
During the first three months, monitoring should be frequent with lab work every 4-6 weeks. Blood pressure monitoring helps catch hypertension early. Regular complete blood count monitoring identifies elevated hematocrit before it becomes problematic.
After stabilization, ongoing monitoring includes lab work every 6-12 months assessing lipid changes, liver and kidney function, and testosterone levels. Annual EKG in men over 50 or those with cardiac risk factors provides reassurance. Some providers recommend periodic echocardiography in men on long-term therapy.
Lifestyle factors deserve equal attention to laboratory monitoring. Consistent cardiovascular exercise improves vascular function and reduces inflammation. Weight management prevents metabolic syndrome. Sleep quality, stress management, and smoking cessation all influence cardiovascular outcomes.
Benefits of Medically Supervised TRT and Risk Mitigation
Medically supervised testosterone therapy offers substantial advantages over unsupervised approaches. Licensed physicians understand testosterone physiology, recognize early warning signs, adjust dosing based on individual response, and prevent dangerous drug interactions.
Men receiving proper treatment experience improved energy, reduced fatigue, improved muscle growth, and better mood, enabling the lifestyle modifications that reduce cardiovascular risk.
Actionable Lifestyle Mitigation Strategies
While clinical monitoring is essential, the most powerful cardiovascular risk reduction during testosterone therapy comes from lifestyle modifications patients can control directly. These strategies work synergistically with medical oversight to lower absolute cardiovascular event risk:
Cardiovascular Exercise Protocol: Men on testosterone therapy should aim for 150 minutes of moderate-intensity aerobic exercise weekly (brisk walking, cycling, swimming) plus 2-3 sessions of resistance training. This combination improves endothelial function, reduces systemic inflammation, and counteracts the HDL-lowering effects of testosterone. Exercise also helps maintain healthy blood pressure and body weight, both critical for cardiovascular safety. Men who maintain consistent aerobic activity during testosterone therapy show better lipid profiles and lower arrhythmia risk than sedentary men on the same therapy.
Dietary Optimization: A Mediterranean-style diet, emphasizing olive oil, fish, vegetables, legumes, and whole grains while limiting processed foods and refined carbohydrates, has demonstrated cardiovascular protective effects in men on hormone therapy. Sodium restriction to under 2,300 mg daily helps prevent hypertension amplification from testosterone. Adequate potassium intake (through leafy greens, bananas, sweet potatoes) supports healthy electrolyte balance and blood pressure regulation. Men should limit alcohol to no more than 1-2 drinks daily, as excessive alcohol consumption combined with testosterone therapy increases arrhythmia risk and elevates triglycerides.
Sleep and Stress Management: Poor sleep quality and chronic stress both increase cardiovascular event risk independently and amplify testosterone-related risks. Men on therapy should prioritize 7-9 hours of consistent sleep nightly and address sleep apnea if present (untreated sleep apnea is a relative contraindication to testosterone therapy). Stress reduction through meditation, yoga, or other relaxation practices measurably lowers blood pressure and reduces inflammation markers in men on testosterone therapy.
Weight Management: Men who maintain a healthy BMI (18.5-24.9) during testosterone therapy experience lower cardiovascular event rates than those who gain weight. Testosterone therapy often increases appetite and can promote fat-free mass gain, but excess caloric intake leads to visceral fat accumulation, which amplifies cardiovascular risk. Tracking caloric intake and maintaining modest caloric balance prevents this common pitfall.
Smoking Cessation: This is non-negotiable. Men who smoke while on testosterone therapy face substantially elevated risk of myocardial infarction and stroke compared to non-smoking testosterone users. The combination of testosterone’s prothrombotic effects and smoking’s endothelial damage creates compounding risk. Smoking cessation should precede or accompany testosterone therapy initiation.
Risk Mitigation Through Dosing and Monitoring Strategy
Risk mitigation in properly supervised therapy involves several key strategies beyond lifestyle. Conservative dosing, using the lowest effective dose rather than maximizing testosterone levels, reduces cardiovascular burden.
Making an Informed Decision About Testosterone Therapy
The decision to pursue testosterone therapy requires honest assessment of your individual risk-benefit ratio. Men with significant hypogonadism, genuinely low testosterone causing symptoms, typically benefit from treatment when baseline screening shows no contraindications. The cardiovascular risks, while real, remain modest in properly screened and monitored populations. The quality-of-life improvements from restoring normal testosterone levels often justify proceeding with appropriate safeguards.
Frequently Asked Questions
Does testosterone replacement therapy increase the risk of heart attack?
The relationship between testosterone therapy and heart attack risk is complex. Historical concerns about myocardial infarction were based on older observational studies, but recent placebo-controlled clinical trials have provided more nuanced findings. Risk depends on baseline cardiovascular health, age, dosage, and monitoring. Men with existing cardiac risk factors require careful baseline screening and ongoing assessment. A qualified physician can evaluate your individual risk profile before starting therapy.
What does the latest clinical research say about TRT and cardiovascular safety?
Recent clinical trials suggest that testosterone therapy’s cardiovascular safety profile depends heavily on patient selection and monitoring. Men without pre-existing cardiovascular disease who receive appropriate dosage monitoring show different risk patterns than those with baseline conditions like peripheral artery disease or left ventricular hypertrophy. Medically supervised TRT with regular serum level checks and cardiac screening is important for patient safety.
How do physicians monitor heart health during testosterone therapy?
Comprehensive monitoring includes baseline screening with blood pressure measurement, lipid panels (including high-density lipoprotein levels), and electrocardiogram assessment before starting therapy. During treatment, physicians track serum testosterone levels and metabolic markers. Regular follow-up appointments assess for potential adverse events. This ongoing monitoring helps detect adverse events early and allows dose adjustment if needed.
Can low testosterone levels contribute to heart disease?
Yes, hypogonadism is associated with increased cardiovascular disease risk. Low endogenous testosterone correlates with metabolic syndrome, reduced vascular health, and higher cardiac risk factors. However, raising testosterone artificially through exogenous administration is not the same as correcting a deficiency. The goal of medically supervised TRT is to restore testosterone to normal therapeutic ranges while managing other cardiovascular risk factors through lifestyle and monitoring.
